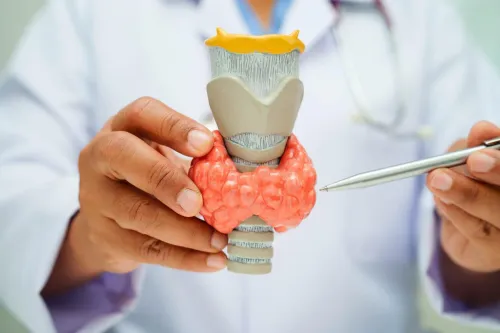
A high calcium result is not enough to choose an operation: you first need confirmed primary hyperparathyroidism, exclusion of familial hypocalciuric hypercalcaemia and an assessment of kidney and bone damage. By the end, you will know which tests to request, when imaging matters, which operation may fit your findings and what to ask a Mumbai surgical team before consenting.
Key takeaways
- Confirm that high calcium and PTH results establish the diagnosis.
- Complete kidney, bone, calcium and vocal-cord assessments before surgery.
- Treat scans as surgical planning tools, not proof of the diagnosis.
- Ask a Mumbai surgeon about complications, conversion and follow-up access.
When does primary hyperparathyroidism justify surgery?
Excess parathyroid hormone (PTH) pulls calcium from bone and reduces its loss through the kidneys, raising blood calcium. This can contribute to kidney stones or nephrocalcinosis, bone thinning, fractures, constipation, nausea, abdominal discomfort, fatigue and poor concentration. These symptoms do not prove that hyperparathyroidism is responsible.
Primary hyperparathyroidism requires elevated albumin-adjusted or ionised calcium with an inappropriately high intact PTH, confirmed through repeat testing. A single high calcium result should not decide surgery or parathyroid treatment in Mumbai. Review vitamin D, kidney function, phosphate and medicines first.
Surgery is commonly considered when primary hyperparathyroidism has any of these features:
- Repeated calcium levels more than 1 mg/dL (0.25 mmol/L) above the laboratory upper limit, particularly with relevant symptoms
- Kidney stones, nephrocalcinosis or significant hypercalciuria above 250 mg/day in women or 300 mg/day in men
- eGFR below 60 mL/min
- Osteoporosis, a vertebral fracture or another fragility fracture
- Age below 50 years
- Selected asymptomatic cases meeting a calcium, kidney or skeletal threshold
Secondary hyperparathyroidism caused by chronic kidney disease and tertiary hyperparathyroidism require a different assessment. The decision must include phosphate, vitamin D, dialysis or transplant status, renal bone disease and medical treatment; primary-hyperparathyroidism thresholds cannot be applied automatically.
Which tests should be completed before a parathyroid operation?
Do not let one high calcium result decide surgery. During a parathyroid surgery consultation, repeat serum calcium and pair it with albumin-adjusted calcium or ionised calcium, then measure intact PTH. Primary hyperparathyroidism requires elevated calcium with inappropriately high PTH on reliable testing.
Complete these checks before choosing an operation:
- Phosphate
- Creatinine and estimated glomerular filtration rate (eGFR)
- 25-hydroxy vitamin D
- Medication review, including thiazide diuretics, lithium, calcium and vitamin D supplements
- Family history, age at diagnosis and previous endocrine tumours
Collect urine for a full 24 hours to measure calcium and creatinine. Use the calcium-to-creatinine clearance ratio (urine calcium × serum creatinine ÷ serum calcium × urine creatinine) alongside the total urine calcium:
| Test or finding | What it helps distinguish | Important limitation |
|---|---|---|
| 24-hour urine calcium | Calcium excretion and kidney-stone risk | Low values do not prove familial hypocalciuric hypercalcaemia (FHH) |
| Calcium-to-creatinine clearance ratio | Low results support FHH; higher results support primary hyperparathyroidism | Vitamin D deficiency, reduced kidney function and medicines can distort it |
FHH is inherited and usually does not improve after gland removal, so discuss uncertain results with an endocrinologist. Young diagnosis, several affected relatives, multigland disease, or pancreatic or pituitary tumours warrants evaluation for MEN1 or another hereditary syndrome; genetic and endocrine findings can change the operation.
How do scans and the planned operation fit together?
If you are searching “parathyroid surgery what to know in mumbai,” treat scans as maps, not proof of disease. Neck ultrasound and technetium-99m sestamibi scanning locate a suspected abnormal gland for operative planning; they do not diagnose hyperparathyroidism. A negative or discordant result does not cancel surgery when calcium and PTH results establish the diagnosis.
Four-dimensional CT can add detail when scans disagree, an ectopic gland is suspected, or a previous operation failed. It also brings more radiation and iodinated-contrast exposure than ultrasound, so it is not a routine replacement for biochemical testing.
| Operation | What it means | When it fits |
|---|---|---|
| Focused parathyroidectomy | Removes the localised gland through a small neck incision | Concordant imaging and a likely single-gland problem |
| Bilateral neck exploration | Examines both sides and assesses multiple glands | Multigland disease, hereditary syndromes, renal secondary or tertiary disease, non-localising scans, or failed previous surgery |
A focused operation can become inadequate if a second abnormal gland appears, particularly with MEN1 or renal disease. Ask how the surgeon will respond.
“Laser parathyroid surgery” is not the usual standard neck approach. Laparoscopic gastrointestinal techniques do not apply to this operation; ask exactly which cervical procedure and evidence a “minimally invasive” label describes.
How should you assess a parathyroid surgeon in Mumbai?
A credible consultation should produce specific answers, not labels such as “advanced” or “minimally invasive.” Ask a parathyroid surgeon in Mumbai to match the proposed operation to your biochemical results, imaging and medical history.
1. Ask about specialist training and documented parathyroid case volume. Request the surgeon’s expected biochemical cure rate and ask how it is measured: normal calcium and PTH after surgery, not simply improved symptoms.
2. Ask why a focused operation is appropriate instead of bilateral neck exploration. Discuss the chance of finding another abnormal gland and converting to bilateral exploration, particularly with non-localising scans, suspected multigland disease or hereditary conditions.
3. Ask whether intraoperative PTH monitoring is available when indicated. Confirm that the team uses the Miami criterion—a fall of at least 50% from the highest relevant baseline about 10 minutes after gland removal—but does not treat that result as a substitute for surgical judgement or postoperative calcium and PTH checks.
4. Discuss recurrent-laryngeal-nerve assessment before and after surgery, pathology review, anaesthesia support, and emergency treatment for neck bleeding, haematoma or hypocalcaemia. Ask who responds if calcium falls rapidly from hungry-bone syndrome.
5. Confirm where follow-up occurs near Mumbai or in your home city, and who reviews abnormal calcium or PTH results. Dr.VinayKumar Thati-Laser & Laparoscopic Surgeon can be compared with other Mumbai providers using this same checklist, rather than choosing on a “laser” or “minimally invasive” claim.
Related service
GI SURGERY Parathyroid Parathyroidectomy (pair-uh-thie-roid-EK-tuh-me) is surgery to remove one or more of the parathyroid glands or a tumor that's affecting a parathyroid... |
Which risks and follow-up arrangements should you accept before consent?
Before you consent, ask how the team will prevent, recognise and manage these operation-specific problems:
- Temporary or permanent hypocalcaemia, including tingling, muscle cramps or spasms from low calcium.
- Recurrent-laryngeal-nerve injury, which can cause a hoarse, weak or breathy voice.
- Bleeding or a neck haematoma, which can threaten the airway and require urgent treatment.
- Persistent hypercalcaemia because an abnormal gland was missed or multiple glands were diseased.
- Recurrent disease after an initial period of documented biochemical cure.
| Finding after surgery | Meaning | What to confirm |
|---|---|---|
| Persistent disease | Hypercalcaemia remains after surgery | Who will investigate missed or multigland disease |
| Recurrent disease | Hypercalcaemia returns after documented normal calcium | When repeat imaging or specialist review begins |
Severe bone disease or markedly raised alkaline phosphatase increases concern for hungry-bone syndrome. Calcium can fall rapidly as bones absorb it, requiring substantial calcium and vitamin D replacement.
Confirm the exact date for repeat calcium and PTH testing, the pathology-report review, and who will manage an abnormal result. Symptom relief does not prove cure.
Reoperation is harder because localisation becomes less reliable and recurrent-laryngeal-nerve injury risk increases. Your first consultation should therefore cover the emergency plan, voice assessment, biochemical follow-up and access to care after you leave Mumbai.
Frequently asked questions
When does primary hyperparathyroidism justify surgery?
Surgery is considered for symptoms or complications such as kidney stones, nephrocalcinosis, osteoporosis or fractures, and for guideline-based findings involving calcium level, kidney function, urine calcium or age. Your surgeon should interpret the results together rather than relying on symptoms alone.
Which tests should be completed before a parathyroid operation?
Ask about repeat calcium with albumin or ionised calcium, intact PTH, phosphate, creatinine with estimated glomerular filtration rate, 25-hydroxy vitamin D, and a 24-hour urine calcium test. A bone density scan and kidney imaging help assess complications. Review medicines such as thiazide diuretics, lithium and biotin because they can affect interpretation.
How do scans and the planned operation fit together?
Ultrasound and sestamibi imaging help locate an abnormal gland and plan a focused operation. They do not confirm primary hyperparathyroidism. Negative or conflicting scans can lead to bilateral neck exploration or additional imaging, depending on the diagnosis and surgeon’s plan.
How should you assess a parathyroid surgeon in Mumbai?
Ask how frequently the surgeon performs parathyroid operations, which procedure is recommended for your results, who provides anaesthesia, and how calcium and voice changes are monitored. Request a clear written estimate, operative plan and pathway for urgent concerns.
Which risks and follow-up arrangements should you accept before consent?
Discuss temporary or permanent low calcium, recurrent laryngeal nerve injury causing voice change, bleeding or neck swelling, persistent or recurrent disease, infection and the possibility of a wider exploration. Confirm postoperative calcium and PTH testing, medication instructions, pathology review and emergency contact arrangements.
Keywords